
Insights







What Do Patients Worry About Unnecessarily? | Dr. Eric Walser
Many men feel alarmed when their PSA comes back above 4. In this short clip, Dr. Eric Walser explains why that number alone can be misleading.
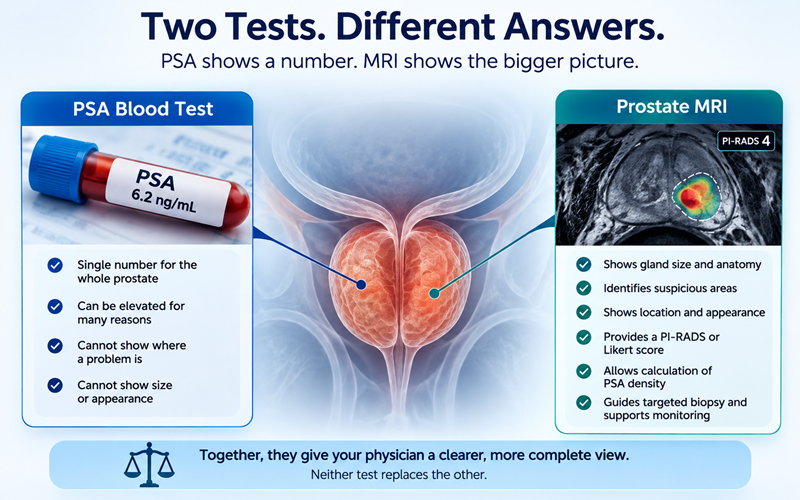
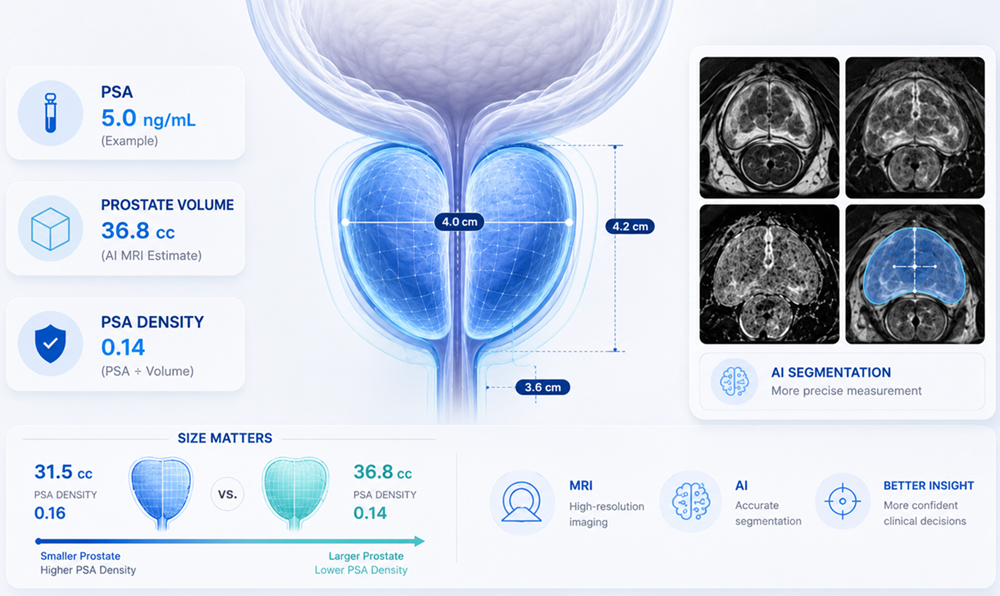
The prostate often grows with age, and a larger prostate tends to produce more PSA (prostate-specific antigen, a blood protein that can rise with cancer and with benign conditions). A PSA that looks high in a man with a small prostate may be expected in a man with a much larger one. Infections, recent procedures, and other non-cancer causes can also raise PSA.
One way physicians put PSA in context is PSA density: the PSA divided by prostate volume, which is often measured on MRI. Using Dr. Walser's examples:
- PSA of 4 with a 20 cc prostate: 4 ÷ 20 = 0.20
- PSA of 8 with a 100 cc prostate: 8 ÷ 100 = 0.08
The second man has the higher PSA but the lower density. PSA density helps place a PSA result into context, but it does not rule cancer in or out on its own. Biopsy decisions often depend on the full clinical picture.
This video is for educational purposes only and is not medical advice. Decisions about screening, biopsy, diagnosis, monitoring, or treatment should be made with your treating physician.
Will Treatment Affect My Sex Life or Bladder Control?
Most men diagnosed with prostate cancer are over 50, and many have partners and active lives they want to protect. In this video, Dr. Eric Walser, former Professor and Chairman of Radiology at the University of Texas and a pioneer in focal ablation for prostate cancer, talks about two concerns men raise most often: sexual function and bladder control.
Dr. Walser explains how standard surgery and radiation can affect sexual function, sometimes for years, and why urinary leakage may weigh even more heavily on daily life. He describes why men tend to feel most satisfied with their choice when treatment has the least impact on their lifestyle. He also discusses how focal therapy aims to limit these side effects for selected men, and why aggressive cancers or cancers that have spread may still require more intensive treatment, such as surgery or hormone therapy.
For most of the history of prostate cancer treatment, the doctors treating it couldn't see it.
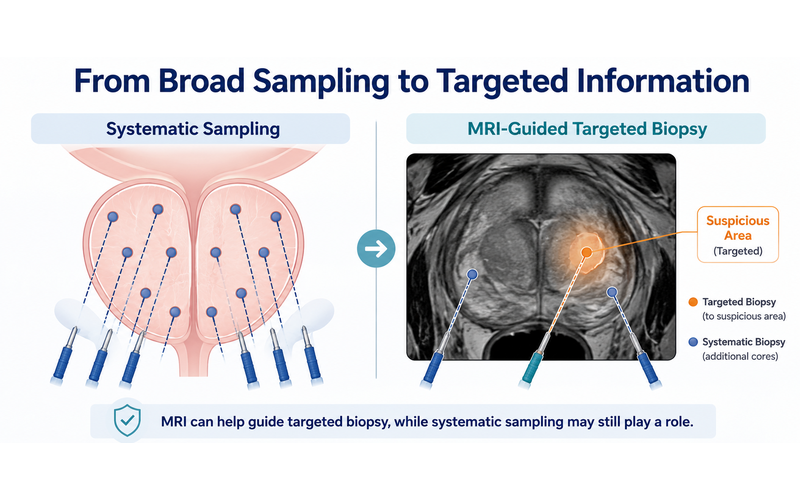
That is the starting point Dr. Eric Walser returns to in this short clip. Before MRI, a rising PSA led to a random biopsy: roughly 12 needles placed across the prostate, hunting for disease no one could actually visualize.
Dr. Walser, former Professor and Chairman of Radiology at the University of Texas and a pioneer in focal ablation of prostate cancer, draws the comparison to mammography. Once you can see a cancer while it is still small, the question changes. Removing the entire prostate is no longer the only reasonable answer, and treating the lesion itself becomes possible for some men.
He is candid that acceptance has been slow. He is also clear about what the shift has meant for patients: shorter procedures, many done as outpatients, and fewer side effects. In his words, "a much better patient-friendly environment now."
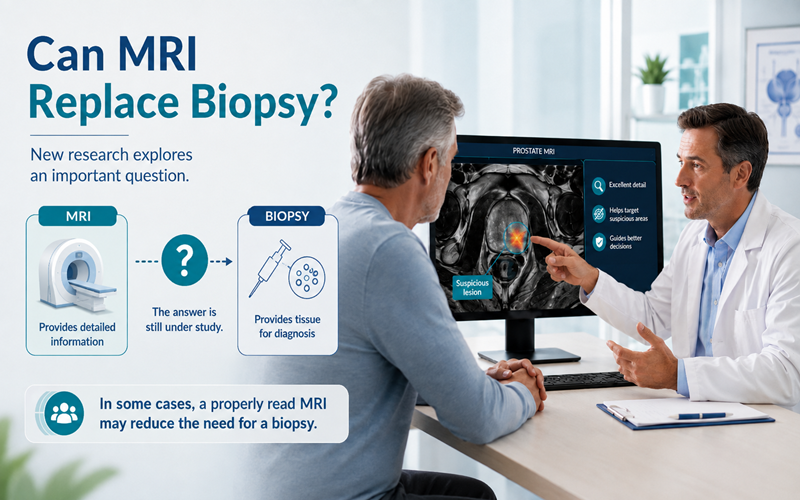
Two things worth adding for anyone reading this while facing their own decisions. Diagnosis still rests on biopsy and pathology, and whether focal treatment is appropriate depends on the full clinical picture and a conversation with your own care team.
What has not changed is that MRI is only as useful as the reading it gets.
"Should I get an AI review of my MRI?"
Dr. Eric Walser, a pioneer in image-guided focal therapy for prostate cancer and BPH and former Professor and Chairman of Radiology at the University of Texas, raised a practical point on this recently.
When a doctor orders a prostate MRI, most patients simply go wherever the referral sends them. Whether that radiology practice uses AI in its reading workflow is largely invisible to the patient. In his words, "for a patient, it's really hit or miss."
His advice is to take control of your own imaging:
Get a copy. Those images belong to you. Ask for them on a disc, or through the download link many imaging centers now provide.
Keep them. If your PSA continues to rise years from now, comparing a new scan against an older one matters. Cancer tends to grow and change over time, while normal prostate tissue generally doesn't. It's the same principle behind comparing this year's mammogram to last year's.
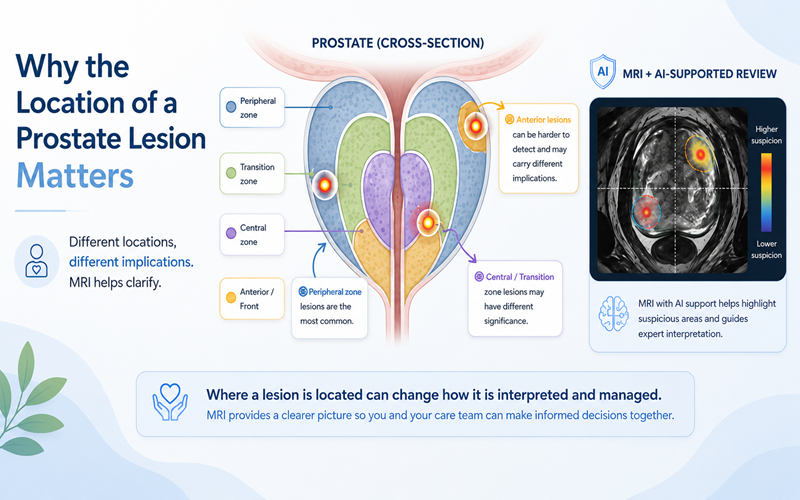
Know your options. If you want a second look, you can send that imaging to a service that will analyze it with AI and return it to you with visual overlays highlighting areas of interest.
One caveat he's clear about: an AI analysis is information, not a decision. Understanding what it means for you, including whether a biopsy or treatment makes sense, still requires a conversation with a physician.
Should you get a second opinion on your prostate MRI?
In this short video, Dr. Eric Walser explains why a second MRI review may be worth considering and how AI can complement an expert's interpretation.
With decades of experience diagnosing and treating prostate disease, Dr. Walser is a recognized pioneer in MRI-guided prostate cancer treatment and the former Chairman of Radiology at the University of Texas
An elevated PSA is not a cancer diagnosis. It is a question mark.
Dr. Eric Walser, a leading authority in image-guided prostate diagnosis and treatment, explains what may happen next and why prostate MRI is increasingly an important early step. Many conditions besides cancer can raise PSA, including an enlarged prostate and inflammation.
Three things worth knowing:
🔹MRI is usually the first step before biopsy: It can help identify possible benign explanations for an elevated PSA and reveal suspicious areas that may need closer evaluation.
🔹AI is helping: Prostate MRI is one of the fastest-growing scans in the country, and it's new enough that many radiologists were never trained specifically on it. AI helps pinpoint the areas that need expert eyes.
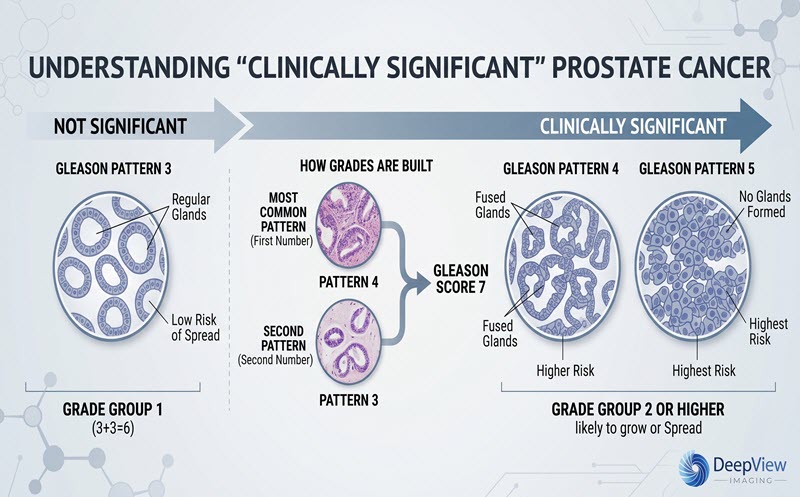
🔹Not every finding requires immediate treatment: Some prostate cancers grow very slowly, and low-grade disease is often monitored through active surveillance. The decision depends on your age, overall health, biopsy results, and the specifics of what was found.
As Dr. Walser explains, this can be a long journey with several important decision points. Having a physician who understands modern prostate cancer care, and asking plenty of questions, can help you make informed decisions together.



Other Articles



